Skip to content
+91 7827219633 All days: 10:00 AM – 6:00 PM info@sehgalivfcentre.com
Recurrent pregnancy loss (RPL)

Recurrent Miscarriage Treatment & Pregnancy Loss Care

Experiencing a miscarriage can be emotionally and physically difficult. When pregnancy loss happens more than once, it's natural to have questions. Recurrent miscarriage does not mean a successful pregnancy is impossible.

Medically reviewed by Dr. Ruchi Malhotra, MBBS, MS (Obstetrics & Gynaecology) · Reg. No. 6111 · Last reviewed October 2026
Counselling room at Sehgal IVF Centre, Delhi

A miscarriage is usually not caused by something you did or failed to do.

At Sehgal IVF Centre, our aim is to identify potentially treatable factors, avoid unnecessary tests or treatments, and give you an individualised plan for a future pregnancy, with care and support at every step.

of patients with recurrent pregnancy loss may have a successful subsequent pregnancy, even without a specific intervention, according to ASRM's 2026 guidance.

Individual outlook varies with factors such as age and the cause of the losses.
What is recurrent pregnancy loss?

Understanding the definition

A miscarriage is a pregnancy that ends before the stage of viability. The term recurrent pregnancy loss is used when losses occur repeatedly. Recurrent miscarriage can have several possible causes, including chromosomal abnormalities, uterine abnormalities, hormonal or metabolic conditions, antiphospholipid syndrome and other factors. In some patients, no specific cause is identified even after appropriate evaluation.

Recurrent pregnancy loss also called recurrent miscarriage · noun

Two or more spontaneous pregnancy losses before 22 completed weeks of pregnancy.

  • Not necessarily consecutive: losses don't have to happen one after another.
  • Includes biochemical pregnancies: very early losses confirmed by blood or urine hCG can be considered.
  • Excludes: confirmed molar and ectopic pregnancies.
Source: ASRM committee opinion, 2026
Recurrent pregnancy loss

Can become pregnant, but pregnancies are lost

A person with RPL may be able to conceive but has difficulty continuing a pregnancy.

≠
Infertility

Difficulty achieving a successful pregnancy

Infertility primarily concerns difficulty achieving pregnancy. A person can have recurrent miscarriage without infertility.

How common is miscarriage?

Miscarriage is unfortunately common, particularly in early pregnancy. Many early miscarriages occur because of chromosomal abnormalities in the developing embryo, which are often random and become more common with increasing maternal age. Having one miscarriage does not necessarily mean there is an underlying problem, but repeated losses may justify a more detailed evaluation.

Why does it happen?

Common causes and risk factors

There is not always one single cause, and in many patients no definite cause is identified (unexplained recurrent pregnancy loss). Current guidance emphasises evidence-based evaluation rather than ordering large numbers of tests or offering treatments that haven't been shown to help. Tap a cause to learn more.

01Chromosomal abnormalities

An important cause of miscarriage, particularly in the first trimester. ASRM's 2026 guidance notes that approximately 50–60% of first-trimester miscarriages are associated with embryonic aneuploidy, and the likelihood increases with maternal age.

Most are random and don't mean either parent has a genetic disorder, but in some recurrent cases testing may identify a chromosomal factor that needs further evaluation.

02Uterine abnormalities

The shape or structure of the uterus can sometimes contribute. Examples include:

  • Uterine septum
  • Submucosal fibroids
  • Endometrial polyps
  • Intrauterine adhesions
  • Other anatomical abnormalities

ASRM recommends uterine-cavity evaluation for patients with unexplained recurrent pregnancy loss.

03Antiphospholipid syndrome (APS)

An autoimmune condition associated with abnormal blood clotting and certain pregnancy complications. Testing may be recommended when your history meets appropriate criteria, and can include:

  • Lupus anticoagulant
  • Anticardiolipin antibodies
  • Anti-beta-2 glycoprotein I antibodies

A positive antibody test doesn't automatically mean APS. Diagnosis needs clinical and laboratory criteria, and some tests may need repeating.

04Thyroid problems

Thyroid disorders can affect reproductive health and pregnancy. Depending on symptoms, history and previous losses, your doctor may recommend tests such as TSH, based on your circumstances rather than every available test.

05Diabetes and metabolic health

Poorly controlled diabetes can affect pregnancy. As part of preconception care, blood glucose and other metabolic factors may be assessed. Good control of existing conditions before pregnancy is an important part of planning.

06Genetic factors

In a small proportion of couples, one partner may carry a balanced chromosomal rearrangement, often without any symptoms. Parental chromosome testing may be considered in selected situations, particularly when miscarriage tissue shows an unbalanced structural abnormality or cannot be tested.

07Male factors

Recurrent pregnancy loss is not only a female health issue. The male partner's age, metabolic health and certain sperm-related factors may be relevant. ASRM discusses an association between elevated sperm DNA fragmentation and RPL, with testing considered in the right clinical context. A standard semen analysis may also be part of assessment. Male infertility

  • Also considered:
  • Certain reproductive or anatomical problems
  • Age-related reproductive changes
  • Other medical conditions
Symptoms

Symptoms of recurrent miscarriage

Recurrent miscarriage itself doesn't have a specific symptom pattern; the main concern is two or more pregnancy losses. During an individual miscarriage, symptoms may include:

  • Vaginal bleeding
  • Abdominal or pelvic cramping
  • Lower back pain
  • Passing tissue or fluid
  • A decrease in pregnancy symptoms

However, bleeding during early pregnancy does not always mean miscarriage.

If you are pregnant now

Seek urgent medical assessment if you experience:

  • Significant bleeding
  • Severe abdominal pain
  • Dizziness or fainting
  • Other concerning symptoms
When to seek help

You don't need to wait for a third loss

You may consider a recurrent pregnancy loss evaluation after two pregnancy losses, rather than necessarily waiting for three. Losses don't need to be consecutive.

A specialist evaluation may be particularly important if you have

  • Two or more miscarriages
  • A previous second-trimester loss
  • History of ectopic or molar pregnancy
  • Known uterine abnormalities
  • Thyroid disease
  • Diabetes
  • Autoimmune disease
  • Previous chromosomal abnormality in pregnancy tissue
  • Family history of genetic disorders
  • Difficulty becoming pregnant
  • Repeated miscarriage despite previous treatment
At Sehgal IVF Centre

Recurrent miscarriage evaluation

Evaluation is individualised, not a one-size-fits-all test panel. Your doctor may review:

Pregnancy history

  • Number of pregnancies
  • Number and timing of miscarriages
  • How each pregnancy was confirmed
  • Ultrasound findings
  • Pregnancy tissue testing
  • Previous pregnancy complications
  • Previous live births

Medical history

  • Thyroid conditions
  • Diabetes
  • Autoimmune conditions
  • Previous infections
  • Medications
  • Previous surgeries
  • Family history
  • Lifestyle factors

Partner's history

Relevant factors from the male partner may also be reviewed. Recurrent pregnancy loss can involve either partner, so a complete assessment may include both.

Investigations

Tests for recurrent miscarriage

Depending on your history, evaluation may include the tests below. Not every patient needs every test.

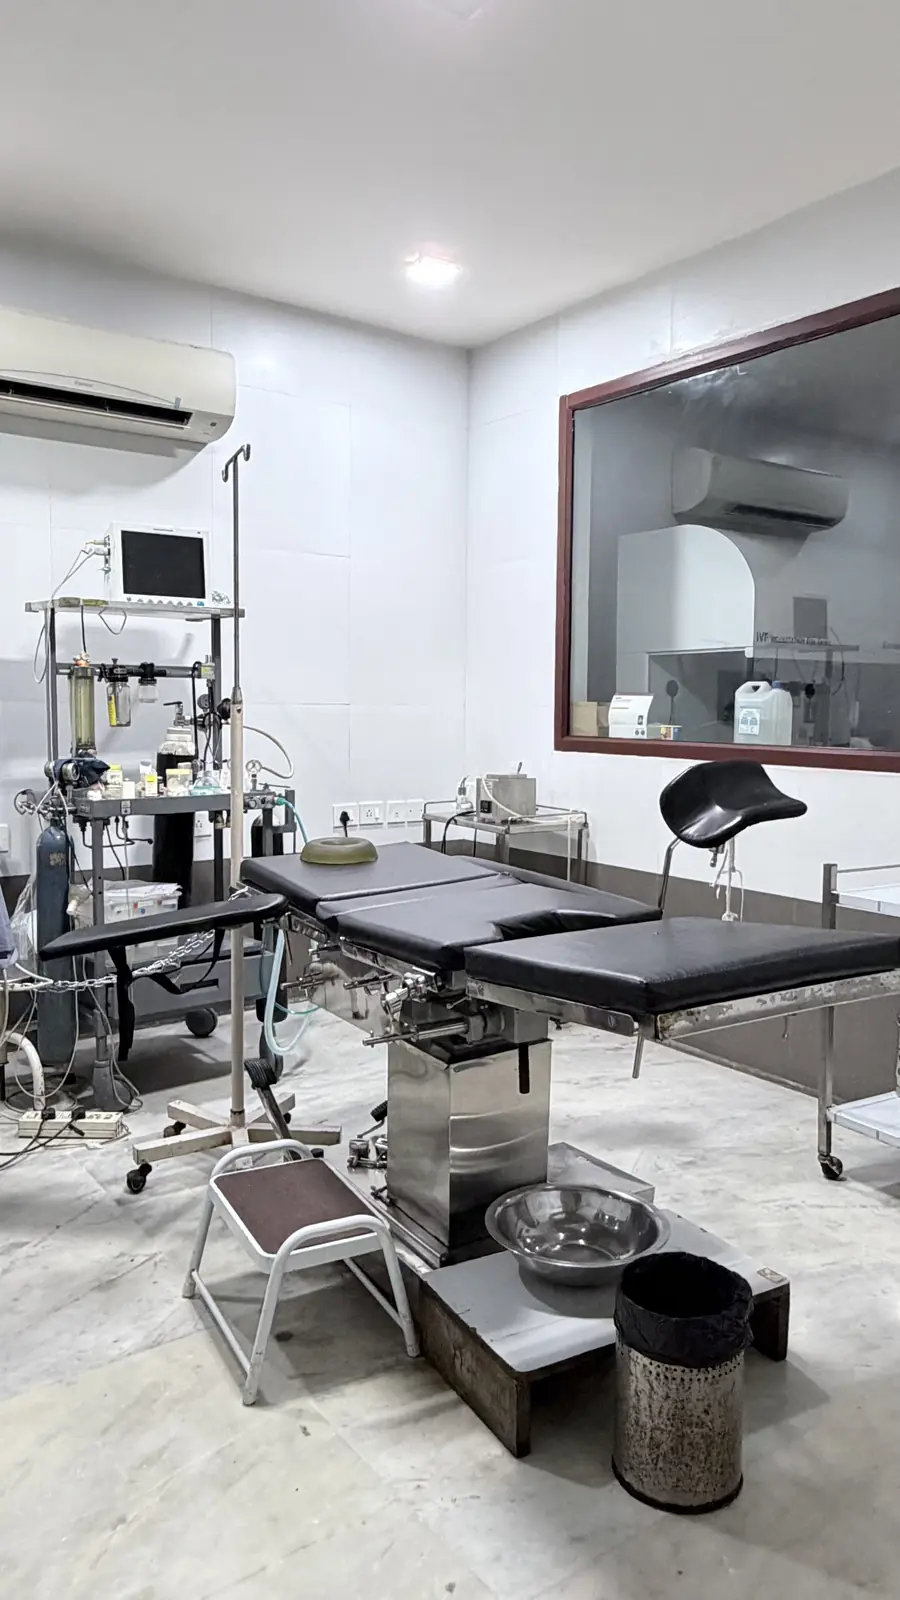
Operation theatre at Sehgal IVF Centre, Delhi
  1. Recommended first step when possible

    Chromosome testing of miscarriage tissue

    When tissue is available and testing is feasible, chromosome analysis can show whether the pregnancy had a chromosome abnormality. ASRM recommends array-based testing of miscarriage tissue as a first step when possible.

  2. Uterine cavity evaluation

    To identify structural abnormalities that may contribute to loss, using methods such as:

    • HSG
    • Saline sonography
    • Hysteroscopy
    • Pelvic imaging
  3. Blood tests

    Depending on your history:

    • Thyroid testing
    • Blood glucose / metabolic testing
    • Antiphospholipid antibodies when indicated
    • Tests based on individual risk
  4. Genetic testing

    Parental karyotyping may be considered in selected cases, particularly when miscarriage testing finds a relevant abnormality or tissue can't be tested. Genetic counselling may be recommended when a chromosomal or inherited condition is suspected.

  5. Male fertility assessment

    May include semen analysis, medical history, lifestyle assessment and, in selected cases, sperm DNA fragmentation testing. Discuss the need for advanced sperm testing with your specialist.

Two or more losses?

Let's look for answers together

A careful, compassionate evaluation can help identify potentially treatable causes and plan for a future pregnancy, without unnecessary tests or treatments.

Reception and waiting lounge at Sehgal IVF Centre, Adarsh Nagar, Delhi
Treatment

Recurrent miscarriage treatment

Treatment depends on the cause identified during evaluation. There is no single medicine or procedure that prevents every miscarriage. Here's how care is matched to what is found:

Uterine abnormality

Treatment of the uterine problem

May include treating a uterine septum, submucosal fibroids, endometrial polyps, intrauterine adhesions or retained pregnancy tissue. ASRM's 2026 guidance states surgical treatment of certain uterine abnormalities may be reasonable. The decision is individualised.

Antiphospholipid syndrome

Medical treatment during pregnancy

If you meet the criteria for APS, treatment may involve medicines such as low-dose aspirin and heparin or another anticoagulant, under medical supervision.

Aspirin and heparin should not be taken simply because you've had miscarriages. ASRM recommends targeted evaluation and evidence-based treatment.

Thyroid or metabolic condition

Thyroid and metabolic management

Appropriate treatment and preconception management of thyroid disease, diabetes or other metabolic conditions may help reduce pregnancy-related risks. Your doctor may recommend optimising these before trying again.

Chromosomal finding

Genetic counselling

Helps explain what the result means, the chance of recurrence, available reproductive options, whether more testing is appropriate, and whether IVF with genetic testing could be considered, based on the specific finding.

Associated infertility or other indication

Fertility treatment when appropriate

Along with pregnancy monitoring and psychological support as part of every plan.

IVF and recurrent miscarriage

IVF is not automatically required

If you can conceive naturally and no infertility factor is present, IVF may not be necessary simply because miscarriages have occurred. It may be considered in selected situations:

  • Associated infertility
  • Certain parental chromosomal rearrangements
  • Need for assisted reproduction for another reason
  • Selected situations where embryo genetic testing is considered
About IVF
PGT-A and recurrent miscarriage

Not a guaranteed treatment

PGT-A can identify some chromosome-number abnormalities in IVF embryos. Because many early miscarriages are chromosomal, it may seem an obvious solution, but it is not guaranteed and not appropriate for every patient. ASRM's 2024 guidance notes the evidence in RPL is complex and doesn't establish it should routinely replace expectant management.

If considered, your doctor should discuss:

  • Age
  • Eggs expected
  • Embryo development
  • Previous miscarriage results
  • Embryos available for testing
  • Benefits
  • Limitations
  • Cost
  • Possibility of no transferable embryo
Prevention

Can recurrent miscarriage be prevented?

Prevention depends on the cause. Some risk factors can be identified and treated, but not every miscarriage can be prevented, as many early losses occur because of random chromosomal abnormalities. A healthy preconception approach may include:

  • Managing existing conditions
  • Avoiding smoking
  • Avoiding recreational drugs
  • Limiting or avoiding alcohol
  • Recommended prenatal supplements
  • A healthy lifestyle
  • Preconception appointments
  • Medical advice on medications

These support reproductive health but cannot guarantee that miscarriage will not occur.

When no cause is found

Unexplained recurrent pregnancy loss

Sometimes a complete evaluation doesn't find a clear cause. This can be frustrating when you want a specific answer, but it does not mean a future successful pregnancy is unlikely. Approximately 50–80% of patients with RPL may have a successful subsequent pregnancy without a specific intervention, although individual prognosis varies.

Your doctor may recommend:

  • Preconception counselling
  • Managing identified health risks
  • Early pregnancy monitoring
  • Supportive care
  • Avoiding treatments without established benefit
Consultation room at Sehgal IVF Centre, Delhi
Emotional support

Your feelings matter too

Recurrent miscarriage can be emotionally difficult. You may experience:

  • Grief
  • Anxiety
  • Fear during a future pregnancy
  • Sadness
  • Anger
  • Guilt
  • Difficulty trusting a pregnancy will progress

It's important to understand that a miscarriage is usually not caused by something you did or failed to do. Ordinary emotional stress is not usually the cause either, but the anxiety that follows loss deserves real support.

ASRM's 2026 guidance emphasises psychological support as an important part of care. Counselling may help, particularly when grief or anxiety is affecting daily life.

Planning ahead

Recurrent miscarriage and future pregnancy

It's understandable to feel anxious about becoming pregnant again. Once pregnancy occurs, your doctor may recommend appropriate early follow-up based on your history.

Before trying again, we may discuss

  1. Results of previous investigations
  2. Treatment of any identified condition
  3. Folic acid / prenatal supplementation
  4. Medication review
  5. Thyroid and metabolic health
  6. Genetic counselling where appropriate
  7. Timing of the next pregnancy
  8. Early pregnancy monitoring
Why choose Sehgal IVF Centre

More than prescribing medicines after every miscarriage

Our care focuses on understanding your previous losses and identifying factors that may be treatable. Where a cause is found, treatment is directed toward it; where none is found, the focus is supportive, evidence-based care and monitoring, not unnecessary treatments.

Our evaluation may include

  • Detailed pregnancy history
  • Review of previous ultrasound reports
  • Review of miscarriage tissue testing
  • Uterine assessment
  • Targeted blood tests
  • Genetic evaluation when appropriate
  • Male-partner assessment
  • Thyroid and metabolic health review
  • Preconception counselling
  • Individualised pregnancy planning

A careful evaluation helps determine whether

  • A cause can be identified
  • The uterus needs assessment
  • Genetic testing is appropriate
  • APS testing is indicated
  • Thyroid or metabolic testing is needed
  • The male partner needs evaluation
  • IVF is actually appropriate
  • Embryo genetic testing should be discussed
  • What monitoring suits a future pregnancy
FAQs

Frequently asked questions about recurrent miscarriage

Still have questions? Call us on +91 7827219633.

What is recurrent miscarriage?

Recurrent miscarriage, also called recurrent pregnancy loss, generally refers to two or more spontaneous pregnancy losses. Current ASRM guidance does not require the losses to be consecutive.

How many miscarriages are considered recurrent miscarriage?

The current ASRM definition uses two or more pregnancy losses. You do not necessarily have to experience three miscarriages before discussing evaluation with a specialist.

Why do recurrent miscarriages happen?

Possible causes include chromosomal abnormalities, uterine abnormalities, antiphospholipid syndrome, thyroid or metabolic problems, genetic factors and some male factors. In many patients, no specific cause is found.

Can recurrent miscarriage be treated?

In some cases, an underlying cause can be identified and treated. For example, certain uterine abnormalities or antiphospholipid syndrome may have specific management options. However, there is no treatment that prevents every miscarriage.

Can I have a successful pregnancy after recurrent miscarriage?

Yes. Many patients with recurrent pregnancy loss subsequently have a successful pregnancy. ASRM's 2026 guidance reports that approximately 50%–80% may have a successful subsequent pregnancy, although individual prognosis varies.

Does recurrent miscarriage mean I cannot have children?

No. Recurrent miscarriage does not mean that having a successful pregnancy is impossible. A fertility specialist can evaluate potential causes and discuss options for a future pregnancy.

Is recurrent miscarriage the same as infertility?

No. Infertility concerns difficulty achieving a successful pregnancy, whereas recurrent pregnancy loss concerns repeated pregnancy losses after conception. A person can have recurrent miscarriage without infertility.

What tests are done after recurrent miscarriage?

Depending on your history, evaluation may include chromosome testing of miscarriage tissue, uterine cavity evaluation, targeted blood tests, thyroid testing when indicated, antiphospholipid antibody testing when appropriate, genetic evaluation and male-partner assessment. Not every patient needs every test.

Can miscarriage tissue be tested?

Yes. When tissue is available and testing is feasible, chromosome analysis can provide useful information about whether the pregnancy had a chromosomal abnormality. Current ASRM guidance recommends array-based chromosome testing of miscarriage tissue when possible.

Can thyroid problems cause recurrent miscarriage?

Thyroid disorders can affect reproductive and pregnancy health. Your doctor may recommend thyroid testing depending on symptoms, risk factors and pregnancy-loss history.

Can PCOS cause recurrent miscarriage?

PCOS may be associated with several reproductive and metabolic factors, but recurrent miscarriage should not automatically be attributed to PCOS. A proper evaluation is needed to identify other possible causes.

Is IVF necessary after recurrent miscarriage?

No. IVF is not automatically required simply because a patient has experienced recurrent miscarriage. It may be considered when infertility or another indication for IVF is present, or in selected genetic circumstances.

Can PGT-A prevent recurrent miscarriage?

PGT-A can identify some chromosome-number abnormalities in embryos created through IVF, but it is not guaranteed to prevent miscarriage and is not routinely appropriate for every patient with recurrent pregnancy loss.

Should both partners be evaluated?

Yes. Recurrent pregnancy loss can involve factors related to either partner, so a complete assessment may include both partners.

Can sperm DNA fragmentation cause recurrent miscarriage?

Some evidence links increased sperm DNA fragmentation with recurrent pregnancy loss. Current ASRM guidance considers sperm DNA fragmentation testing in selected patients with recurrent unexplained pregnancy loss rather than as a universal test.

Should I take aspirin after recurrent miscarriage?

Do not start aspirin on your own. Aspirin may be appropriate in certain medical situations, such as specific cases of antiphospholipid syndrome, but it is not a universal treatment for recurrent miscarriage. Discuss it with your fertility specialist.

Should I take progesterone after recurrent miscarriage?

Progesterone treatment is not appropriate for every patient with recurrent miscarriage. Whether it has a role depends on the clinical situation and pregnancy history. Your doctor should decide whether progesterone is appropriate rather than using it routinely without assessment.

Can stress cause recurrent miscarriage?

Miscarriage is usually not caused by ordinary emotional stress or something a woman did or failed to do. After recurrent miscarriage, however, emotional stress and anxiety can be significant and deserve appropriate support.


Book a recurrent miscarriage consultation

More than one loss is deeply upsetting, but a successful pregnancy is still possible

A detailed evaluation can help identify potentially treatable causes and determine whether additional testing or treatment is appropriate. If you've experienced two or more pregnancy losses, speak with a fertility specialist about evaluation and planning for a future pregnancy.

Medically reviewed

Dr. Ruchi Malhotra, MBBS, MS (Obstetrics & Gynaecology)
Medical registration no. 6111

Last reviewed: October 2026 · Last updated: October 2026

Medical disclaimer: This page is intended for general educational purposes and does not replace medical consultation, diagnosis or treatment. Recurrent pregnancy loss can have different causes, and sometimes no specific cause is identified. Testing and treatment should be individualised by a qualified fertility or reproductive-medicine specialist. If you have experienced recurrent miscarriage or are currently pregnant and have concerning symptoms, seek appropriate medical care.

Call now Book consultation